
If every step feels like a negotiation with your knee, you’re not alone. Knee pain from arthritis affects millions of people worldwide, and for many, everyday activities like climbing stairs, walking to the market, or getting out of a chair become a struggle. For those whose pain no longer responds to other treatments, knee replacement surgery can be life-changing.
Here’s a plain-language guide to what it involves.
What Is a Knee Replacement?
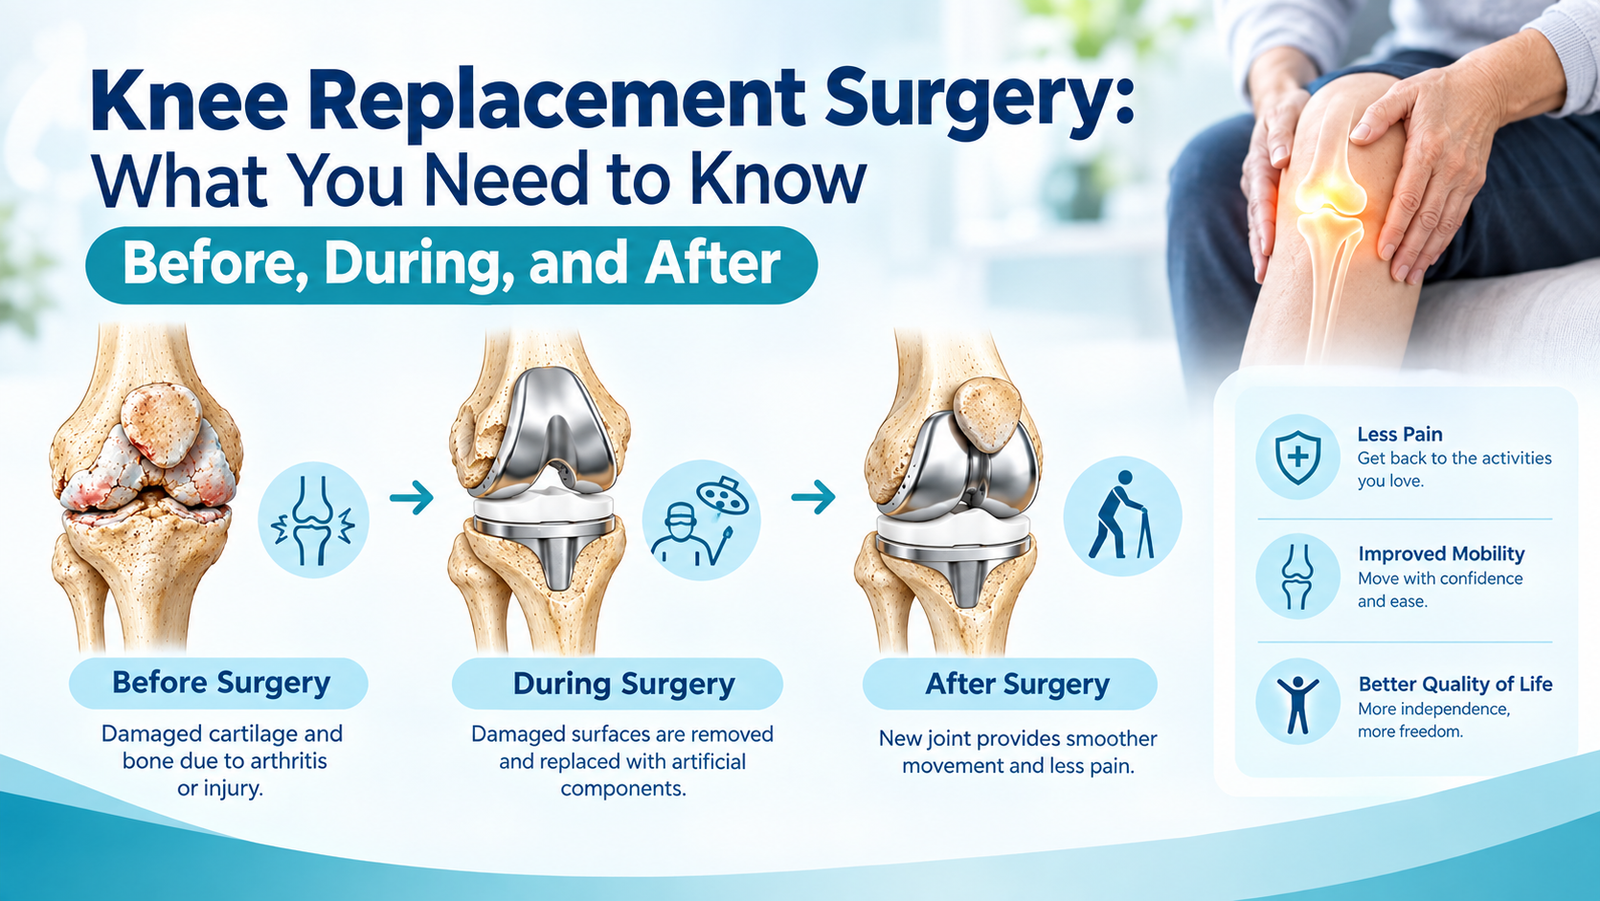
Your knee joint is where the thigh bone (femur), shin bone (tibia), and kneecap (patella) meet. Each surface is coated with smooth cartilage that lets the bones glide painlessly. When that cartilage wears away, bone rubs against bone, causing pain, stiffness, and swelling.
In a knee replacement (also called knee arthroplasty), a surgeon removes the damaged surfaces and replaces them with artificial components made of metal alloys and medical-grade plastic. The result is a joint that moves smoothly again, without the painful friction.
Who Needs One?
Osteoarthritis is the most common reason, but rheumatoid arthritis, post-traumatic arthritis after an injury, and some other conditions can also damage the joint. Surgery is usually considered when:
- Pain persists despite medication, physiotherapy, weight management, and injections
- Pain disturbs your sleep or limits basic daily activities
- Stiffness, swelling, or deformity (such as bowing of the legs) is worsening
- X-rays show significant joint damage
Age alone isn’t the deciding factor. The question is how much the knee is affecting your quality of life.
Types of Knee Replacement
Total knee replacement: All three compartments of the joint are resurfaced. This is the most common type.
Partial (unicompartmental) knee replacement: Only the damaged part of the knee is replaced. It suits people whose arthritis is limited to one area, and recovery can be quicker.
Robotic-assisted knee replacement: Not a separate type of implant, but a technique in which robotic systems help the surgeon plan and execute bone cuts with precision. Its long-term advantages over conventional surgery are still being studied, so it’s worth discussing with your surgeon.
What Happens During Surgery?
The operation typically takes one to two hours and is done under spinal or general anesthesia. The surgeon makes an incision, removes the damaged bone and cartilage, fits the artificial components, and checks that the knee bends and straightens properly before closing. Most patients stay in the hospital for a few days, though same-day or next-day discharge is becoming more common in some centers.
Recovery: What to Expect
Recovery is a partnership between you, your surgeon, and your physiotherapist, and rehab matters as much as the surgery itself.
- Day 1: You’ll usually be encouraged to stand and take a few steps with support. Early movement reduces the risk of blood clots and stiffness.
- First 2 weeks: Expect swelling, bruising, and discomfort. You’ll do daily exercises, use a walker or crutches, and manage pain with prescribed medication and ice.
- 6 to 12 weeks: Most people walk independently, return to light activities, and may resume driving once cleared by their doctor.
- 3 to 6 months: Strength and endurance improve significantly. Many people feel close to their new normal.
- Up to a year: Swelling and minor aches can linger, and gains continue gradually.
Tips for a Smoother Recovery
- Do your exercises. Skipping physiotherapy is the most common reason for a poor outcome.
- Prepare your home. Remove loose rugs, add grab bars in the bathroom, and arrange a comfortable seat with a raised height.
- Control swelling. Elevate your leg and use ice as advised.
- Eat well and stay hydrated. Protein, vitamins, and adequate fluids support healing.
- Stay patient. Progress isn’t always linear, and good days and bad days are normal.
Risks and Limitations
Knee replacement is generally safe and effective, but like any major surgery it carries risks, including infection, blood clots, stiffness, persistent pain in a minority of patients, and, over time, loosening or wear of the implant. Your surgeon will review these with you based on your health, age, and medical history.
Modern implants often last 15 to 20 years or more, though this varies with age, weight, activity level, and surgical factors. High-impact activities like running and jumping sports are generally discouraged, while walking, swimming, cycling, and golf are usually fine.
Are There Alternatives?
Surgery isn’t the first step. Before it, many people try weight loss, physiotherapy, strengthening exercises, walking aids, anti-inflammatory medications, and joint injections such as corticosteroids or hyaluronic acid. These can help delay or sometimes avoid surgery, especially in earlier stages of arthritis.
Making the Decision
Deciding on surgery is personal. Ask yourself: How much is knee pain limiting my life? Have I tried the non-surgical options? Am I ready for the commitment of rehabilitation? Then talk with an orthopedic surgeon, get your questions answered, and consider a second opinion if you’re unsure.
For many people, the answer is a clear yes. After recovery, they return to walking, traveling, playing with grandchildren, and living without constant pain.
This article is for general information only and isn’t a substitute for professional medical advice. Please consult a qualified orthopedic surgeon about your own situation.